
 See Our Latest Article on HelloNation

What usually happens during a first chiropractic visit?
A first chiropractic visit generally includes a health history, discussion of the main concern, a physical examination, and a review of possible next steps. The purpose is to understand whether chiropractic care is appropriate and safe—not simply to begin treatment immediately.
The visit may take longer than later appointments because the chiropractor needs information about symptoms, past injuries, medical conditions, medications, daily activities, and personal goals. Some offices may also ask about sleep, work posture, exercise, and activities that make symptoms better or worse.
A first visit may or may not include hands-on treatment. That decision depends on the examination findings, the person’s health history, and whether there are warning signs that require medical evaluation instead.
What should you bring or prepare beforehand?
Bring a list of current medications, relevant medical records, and information about previous injuries or treatments. If imaging reports or test results relate directly to the problem, they may also be useful.
Before arriving, it can help to think about:
- When the symptoms began
- Whether the problem started suddenly or gradually
- What movements, positions, or activities affect it
- Whether pain travels into an arm or leg
- Any numbness, tingling, weakness, dizziness, or balance changes
- Previous falls, vehicle collisions, surgeries, or fractures
- Existing conditions such as osteoporosis, arthritis, inflammatory disease, or cancer
- Recent illnesses, fever, unexplained weight loss, or significant fatigue
Comfortable clothing is usually practical, particularly if the examination involves the neck, back, shoulders, hips, or legs. Clothing that allows normal movement is often more useful than restrictive garments.
What questions will the chiropractor ask?
The history-taking portion is designed to identify patterns and possible causes, as well as conditions that may need a different type of care. Questions may cover the location, intensity, and timing of symptoms.
A chiropractor may ask whether pain is constant or intermittent, whether it affects sleep, and whether it changes with sitting, standing, walking, lifting, coughing, or turning. The discussion may also include work demands and household routines.
For residents managing winter conditions, symptoms may be connected to shoveling, slipping on ice, carrying salt or firewood, or spending more time indoors in fixed positions. In warmer months, gardening, cycling, yard work, and recreational activities can create different physical demands. These details help place symptoms in context without assuming that every problem has the same cause.
The chiropractor should also ask about health factors that can change the safety of certain techniques. A complete answer matters even when a condition seems unrelated to back or neck discomfort.
What does the physical examination involve?
The examination usually involves observation, movement testing, and basic neurological or orthopedic checks. The chiropractor may assess posture, walking, joint range of motion, muscle strength, reflexes, sensation, and tenderness.
You may be asked to bend, rotate, walk, raise an arm, or perform another simple movement. The goal is to see how the body moves and whether a particular position reproduces symptoms.
The examination should be explained in understandable terms. You should be able to ask what a test is checking and tell the chiropractor if a movement causes sharp, worsening, or unfamiliar pain.
An examination is not the same as a diagnosis based on appearance alone. Posture can provide useful information, but it does not explain every cause of pain. A careful assessment considers symptoms, medical history, movement findings, and other relevant factors together.
Will imaging be ordered?
Not everyone needs an X-ray, MRI, or other imaging during a first visit. Imaging is generally considered when the results are likely to change the evaluation or treatment plan, or when there is concern about a fracture, serious disease, significant nerve involvement, or another condition requiring further investigation.
Routine imaging for uncomplicated back or neck pain may not provide useful information and can sometimes reveal age-related changes that are not the source of symptoms. The decision should be based on the individual situation rather than on a standard requirement for every new patient.
If imaging is suggested, reasonable questions include:
- What concern is the imaging intended to evaluate?
- How would the result change the plan?
- Is the imaging urgent?
- Are prior images or reports sufficient?
- Would another medical evaluation be more appropriate?
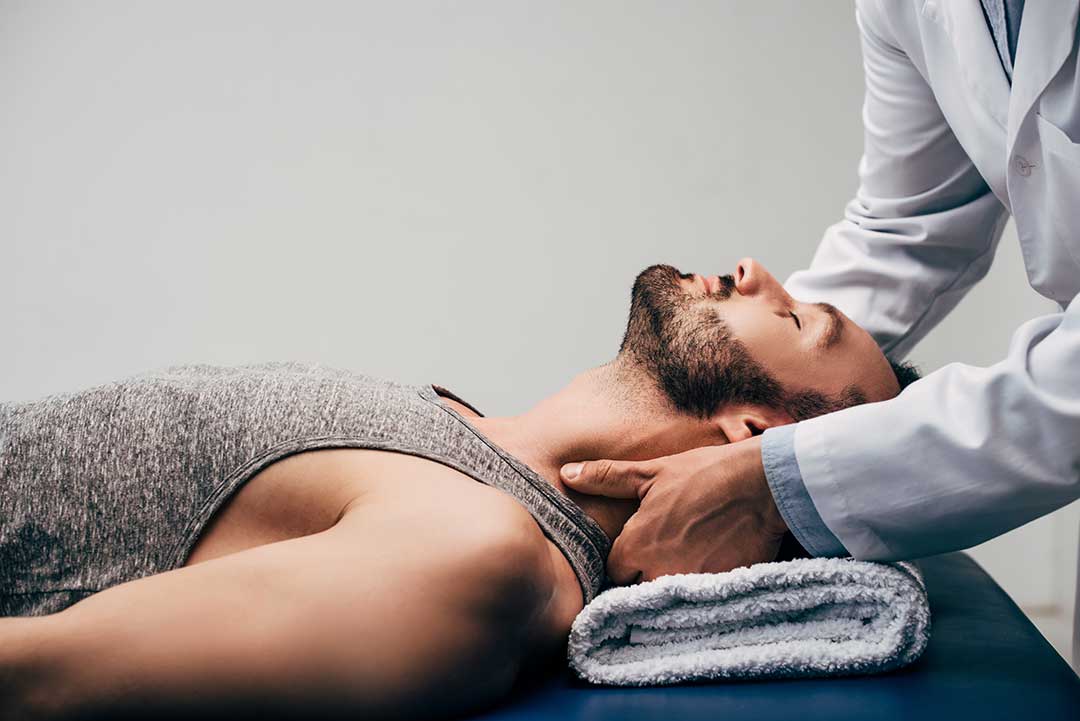
What happens if treatment is offered that day?
If treatment is considered appropriate, the chiropractor should explain what will be done, why it may help, and what sensations or short-term effects are possible. Treatment might include manual techniques, joint mobilization, soft-tissue work, stretching, exercise instruction, or advice about movement and activity.
A spinal adjustment is not automatically required during a first visit. It should be voluntary and based on an informed discussion. You can ask to begin with examination, education, or gentler movement-based care if that feels more comfortable.
A person should not feel pressured to accept a technique that has not been explained. It is reasonable to ask about alternatives, expected benefits, possible risks, and what to do if symptoms worsen afterward.
Temporary soreness can occur after some forms of manual treatment, much like the discomfort that may follow unfamiliar exercise. Severe, progressive, or unusual symptoms should not be dismissed as a normal response.
What are the warning signs that may change the plan?
Certain symptoms require medical assessment rather than routine chiropractic treatment. Urgent attention may be appropriate for new loss of bladder or bowel control, numbness around the groin or inner thighs, rapidly increasing weakness, severe unsteadiness, or major symptoms after a significant fall or collision.
Other concerns that deserve prompt medical discussion include fever with severe back pain, unexplained weight loss, a history of cancer, severe pain that does not change with position, or symptoms that began after a substantial injury. People with fragile bones, blood-clotting problems, vascular conditions, or recent surgery may need additional precautions.
Neck symptoms accompanied by sudden severe headache, fainting, vision changes, difficulty speaking, facial drooping, or one-sided weakness should be treated as a medical emergency. These signs are not appropriate for routine musculoskeletal care.
What should you expect at the end of the visit?
By the end of the first visit, you should have a clearer explanation of the working assessment, what has and has not been established, and what the next step involves. The plan may include home exercises, activity adjustments, monitoring, additional evaluation, or treatment over time.
A useful plan should identify what improvement would look like and when the situation should be reassessed. It should also explain which symptoms would require a change in direction.
Care should fit real life. Someone living in a multi-level home may need advice about stairs and lifting laundry; someone working at a desk may need strategies for changing positions; and someone responsible for outdoor maintenance may need guidance on pacing seasonal tasks. Practical details often matter as much as the examination findings.
The first visit is also an opportunity to decide whether communication feels clear and respectful. You should leave knowing what was found, what remains uncertain, and what choices are available.
